
Recurrent pityriasis rosea: challenging the one-time rash paradigm (case report)
Prita Hejib, Anita Sajjanar, Sunita Vagha
Corresponding author: Prita Hejib, Department of Pathology, Jawaharlal Nehru Medical College, Datta Meghe Institute of Higher Education and Research, Sawangi Meghe, Wardha, India 
Received: 15 Sep 2025 - Accepted: 03 Jul 2026 - Published: 09 Oct 2026
Domain: Histopathology,Pathology
Keywords: Pityriasis rosea, recurrence, skin lesions, case report, papillosquamous rash
Funding: This work received no specific grant from any funding agency in the public, commercial, or non-profit sectors.
©Prita Hejib et al. Pan African Medical Journal (ISSN: 1937-8688). This is an Open Access article distributed under the terms of the Creative Commons Attribution International 4.0 License (https://creativecommons.org/licenses/by/4.0/), which permits unrestricted use, distribution, and reproduction in any medium, provided the original work is properly cited.
Cite this article: Prita Hejib et al. Recurrent pityriasis rosea: challenging the one-time rash paradigm (case report). Pan African Medical Journal. 2026;55:71. [doi: 10.11604/pamj.2026.55.71.49382]
Available online at: https://www.panafrican-med-journal.com//content/article/55/71/full
 PDF in process
Case report 

Recurrent pityriasis rosea: challenging the one-time rash paradigm (case report)
Recurrent pityriasis rosea: challenging the one-time rash paradigm (case report)
 Prita Hejib1,&, Anita Sajjanar2, Sunita Vagha1
&Corresponding author
Pityriasis rosea (PR) is traditionally considered a self-limiting papulosquamous dermatosis, typically presenting as a single episode. Recurrence is deemed rare, and thus often overlooked in clinical practice. However, emerging case reports and observational data suggest that Pityriasis rosea may not be as strictly monophasic as previously believed. The aim is to highlight and analyse the phenomenon of recurrent Pityriasis rosea, challenging the conventional paradigm of it being a one-time rash, and to discuss potential etiological factors, diagnostic dilemmas, and management strategies.

Pityriasis rosea is a type of papulo-squamous skin condition that predominantly affects individuals between 10 and 35 years of age. Typically, it starts with a solitary lesion known as the "herald patch," which is then followed within one to two weeks by multiple pink, scaly eruptions on the skin. While the exact cause remains unclear, the pattern of symptoms and immune response suggests a possible viral origin.
Recurrent presentations may pose diagnostic challenges, especially in differentiating it from drug-induced eruptions or other dermatoses. Understanding the features of recurrent cases is important to avoid misdiagnosis and unnecessary treatments.
Pityriasis rosea is generally a self-limiting skin condition with a recurrence rate reported to be around 3-5%. Recurrent pityriasis rosea is uncommon, and multiple recurrences are even rarer, with only a few case reports documented. Although Robert Willan identified pityriasis rosea as early as 1798, it was not formally described until 1860 by the French physician Camille Melchior Gilbert.

Patient information: a young 23-year-old female presented with complaints of itching all over the body for 1-2 months. The patient has no comorbidities; her medical history was unremarkable, and she was not on any medication.
Clinical findings: physical examination revealed multiple erythematous papules and well-defined plaques with scaling at the border of varying size present discretely over the back (Figure 1). There were no lesions present over the mouth or face.
Timeline of current episode: on examination, the patient presented with a fresh papulosquamous rash affecting the face, neck, trunk, upper limbs, and thighs. A larger plaque with a peripheral collarette of scales was noted on the mid-abdomen. A diagnosis of pityriasis rosea was made. Two weeks later, the patient developed a similar mildly itchy, scaly rash involving the trunk, upper limbs, and thighs. In this episode, a herald patch had emerged on the mid-abdomen a few days prior to the appearance of smaller scaly lesions. As with the previous episode, there was no preceding illness or introduction of new medications.
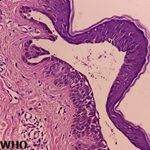
Diagnostic assessment: laboratory analysis revealed the patient's full blood count was normal, and a normal erythrocyte sedimentation rate of 12mm/hr was observed. Serological examination revealed that she was negative for syphilis and antibodies to human immunodeficiency virus, and microscopic examination showed that the patient did not exhibit any signs of fungal infection. The patient's C-reactive protein (CRP) level was 16.2mg/L. A 5mm skin punch biopsy was taken from the right upper back region and sent for histopathological examination. Sections from the skin biopsy show mild perivascular inflammatory infiltrate seen with evidence of abundant lymphocytes (Figure 2), parakeratosis and focal spongiosis (Figure 3, Figure 4 and Figure 5).
Diagnosis: a few of the possible diagnoses were as follows: tinea corporis (superficial dermatophytosis); secondary syphilis; drug-induced eruptions (PR-like drug reactions); nummular eczema and lichen planus (annular or papulosquamous types).
Therapeutic interventions: the patient was started on a two-week course of oral erythromycin 500mg four times daily and topical betamethasone valerate 0.05% cream applied twice daily. After a two-week follow-up and final diagnosis, the patient was treated with acyclovir 400mg three times a day for a week and topical betamethasone valerate 0.05% cream.
Follow-up and outcome of interventions: at follow-up after two weeks, there was no improvement in the rash. Repeat full blood count results were within normal limits. Herpes simplex virus testing from oral ulcer samples returned negative. A repeat skin biopsy revealed mild hyperkeratosis with focal parakeratosis, focal spongiosis, and lymphocytic exocytosis. Apoptotic keratinocytes and focal basal vacuolar changes were also noted, along with a mild superficial perivascular lymphocytic infiltrate. These findings supported the diagnosis of Recurrent Atypical Pityriasis rosea.
Patient perspective: when the rash first appeared, its rapid spread and associated itching were quite distressing. Receiving a definite diagnosis of pityriasis rosea from my doctor was reassuring, particularly after understanding that it is a self-limiting condition. The treatment plan — mainly soothing creams and antihistamines to control the itching — eased my discomfort and made the rash easier to manage as it resolved. Regular check-ups and clear guidance on skin care made me feel well supported throughout the recovery process. Although it took several weeks for the rash to disappear completely, the care I received helped reduce my anxiety and improved my ability to cope. Being informed about the possibility of recurrence has also made me more confident in recognising early symptoms should it reappear.
Informed consent: informed consent was obtained from the patient prior to performing skin biopsy.
Pityriasis rosea is an acute, self-limiting papulosquamous skin disorder, most commonly affecting adolescents and young adults. It typically begins with a solitary lesion known as the "herald patch," followed by a generalised secondary eruption along skin cleavage lines [1]. While the condition is generally benign and resolves within 6 to 8 weeks, recurrences are uncommon and reported in a small percentage of cases. The exact cause of pityriasis rosea remains uncertain, though a viral aetiology—particularly reactivation of human herpesvirus 6 or 7—has been proposed based on clinical and immunological evidence.
Diagnosis is primarily clinical, based on the typical morphology and distribution of lesions. However, atypical presentations can occur, including inverse, vesicular, purpuric, or papular variants, which may complicate recognition. In such cases, dermoscopy, histopathology, or serological investigations may be used to exclude mimickers such as secondary syphilis, tinea corporis, drug eruptions, and guttate psoriasis.
Few studies reported by Singh et al. show evidence of recurrences up to 5 episodes in four years [2]. Typical eruptions of pityriasis rosea last 6-8 weeks, although durations as short as two weeks and as long as five months have also been reported. According to Björnberg and Hellgren, only 2.8% of patients relapse [3]. However, Halkier-Sørensen reported a patient in whom relapses were observed annually for five consecutive years. Second attacks of pityriasis rosea are said to occur after an interval of a few months or many years [4]. Drago et al. in their study of 430 patients, found that pityriasis rosea relapsed within 18 months in 3.7% of patients [5]. A similar study done by Zawar and Kumar documented recurrences of 4 episodes in a year [6]. The description of every patch appeared is stated as follows (Table 1). However, the authors added that this relapse rate was probably an underestimation given that it was rare that the same doctor who made the original diagnosis would also be the doctor who observed the relapse in the patient. This state of affairs may partly explain the lack of reports on multiple recurrences of pityriasis rosea in the literature.
Recurrent pityriasis rosea, though uncommon, represents a clinically significant variation of a condition traditionally regarded as self-limiting and non-recurrent. Its occurrence highlights the need for heightened clinical awareness to distinguish repeat episodes from other dermatoses that mimic PR. Early recognition can prevent misdiagnosis, reduce unnecessary investigations, and provide reassurance to patients experiencing repeated rashes [7,8]. Educating patients about the possibility of recurrence may also help alleviate anxiety and encourage timely consultation. Further studies exploring the underlying triggers and pathophysiological mechanisms of recurrence are warranted to enhance understanding and guide evidence-based management strategies.
The authors declare no competing interests.
Prita Hejib: conceptualised and designed the study, collected patient data, and contributed to manuscript drafting. Anita Sajjanar: assisted in data analysis, literature review, and preparation of the discussion section. Sunita Vagha: supervised clinical evaluation, verified diagnostic findings, and provided critical revisions to the manuscript. All authors read and approved the final version of the manuscript.
The authors express their sincere gratitude to the patient who participated in this study for her cooperation and trust. We also thank the clinical and nursing staff of the dermatology department for their valuable assistance in patient care and follow-up. The authors acknowledge the support of the institutional ethics committee for their guidance and approval.
Table 1: review of literature of case reports of pityriasis rosea
Figure 1: skin lesions showing multiple erythematous papules, well defined plaques with scaling at the border of varying size present discretely over back
Figure 2: low power view of microscopy skin lesion showing spongiosis, perivascular lymphocytic infiltrate
Figure 3: low power view of microscopy skin lesion showing spongiosis and acanthosis with parakeratosis and superficial perivascular lymphocytic infiltrate
Figure 4: high power view of microscopy skin lesion showing spongiosis and accumulation of fluid between the cells of the epidermis leading to separation of keratinocytes, forming visible gaps
Figure 5: high power view of microscopy skin lesion showing parakeratosis and retention of nuclei within the cells of the stratum corneum (outermost layer of the epidermis)
- Wood GS, Reizner G. Other papulosquamous disorders. Dermatology. 2003;2:137-48. Google Scholar
- Singh SK, Singh S, Pandey SS. Recurrent pityriasis rosea. Indian J Dermatol Venereol Leprol. 1998 Sep-Oct;64(5):237. PubMed | Google Scholar
- Björnberg A, Hellgren L. Pityriasis rosea. A statistical, clinical, and laboratory investigation of 826 patients and matched healthy controls. Acta Derm Venereol Suppl (Stockh). 1962;42(Suppl 50):1-68. PubMed | Google Scholar
- Halkier-Sørensen L. Recurrent pityriasis rosea. New episodes every year for five years. A case report. Acta Derm Venereol. 1990;70(2):179-80. PubMed | Google Scholar
- Drago F, Broccolo F, Rebora A. Pityriasis rosea: an update with a critical appraisal of its possible herpesviral etiology. J Am Acad Dermatol. 2009 Aug;61(2):303-18. PubMed | Google Scholar
- Zawar V, Kumar R. Multiple recurrences of pityriasis rosea of Vidal: a novel presentation. Clin Exp Dermatol. 2009 Jul;34(5):e114-6. PubMed | Google Scholar
- Yüksel M. Pityriasis rosea recurrence is much higher than previously known: a prospective study. Acta Derm Venereol. 2019 Jun 1;99(7):664-667. PubMed | Google Scholar
- Li A, Li P, Li Y, Li W. Recurrent pityriasis rosea: a case report. Hum Vaccin Immunother. 2018 Apr 3;14(4):1024-1026. PubMed | Google Scholar
Search
This article authors
On Pubmed
On Google Scholar
Citation [Download]
Navigate this article
Similar articles in
Key words
Tables and figures



Article metrics
Recently from the PAMJ





Authors´ services
