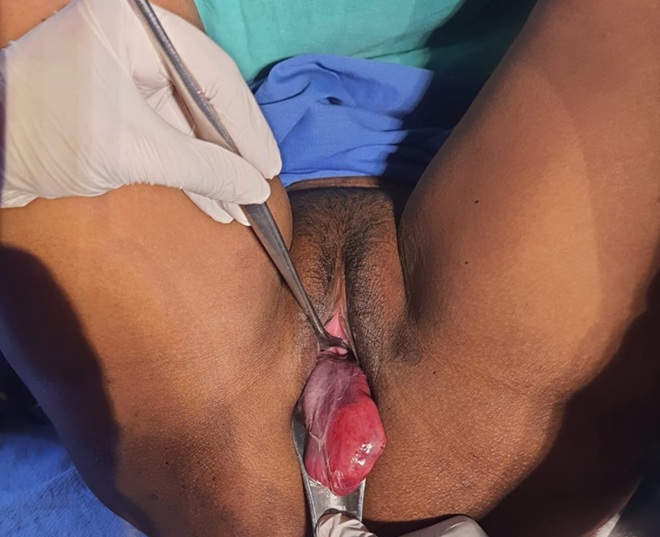
A 35-year-old multiparous woman presented with complaints of a fleshy mass protruding through the vaginal opening for several days, associated with foul-smelling discharge, pelvic discomfort, and occasional bleeding. The mass was reported to increase in size on straining and was associated with difficulty in sitting and walking. There was no prior history of gynaecological surgery, but the patient had a history of heavy menstrual bleeding over the past few months. On perineal examination, a well-defined, smooth, congested, reddish mass was seen protruding outside the vaginal introitus. The mass appeared pedunculated, arising from within the uterine cavity and appeared to be connected through the cervical canal. The surface was edematous with areas of congestion, suggestive of compromised blood supply. The cervix was partially dilated, allowing passage of the mass, while the vaginal walls were otherwise normal and not everted. The uterus was not completely prolapsed. Surrounding skin showed mild irritation due to discharge, but no frank ulceration was noted. Bimanual and gynaecological assessment suggested that the mass was not arising from the vaginal wall itself. Clinical findings were consistent with a prolapsed submucosal uterine fibroid (fibroid polyp) that had extruded through the cervix into the vagina. The condition was likely precipitated by multiparity and chronic uterine contractions associated with fibroid expulsion. Systemic examination did not reveal any significant comorbidities. Management focused on stabilisation, infection control, and definitive surgical removal of the fibroid. Vaginal myomectomy was planned, with further evaluation of the uterine cavity to rule out additional fibroids.
Corresponding Author
Pranjali Jode, Smt. Radhikabai Meghe Memorial College of Nursing, Datta Meghe Institute of Medical Science (DU), Wardha, India (pranjalijode@gmail.com)